
MRCOG Part 1 · Anatomy · Reproductive Organs
Uterus: MRCOG Part 1 questions and key facts
The uterus is a central pelvic reproductive organ composed of a muscular corpus and a fibrous cervix, joined by the isthmus. Understanding uterine anatomy is critical for MRCOG Part 1, particularly its vascular supply, support apparatus, and lymphatic drainage patterns. In women of reproductive age, the corpus-to-cervix ratio is two to one, regressing to one to one following menopause. The organ is supported by condensed endopelvic fascial ligaments, notably the cardinal and uterosacral ligaments, while the round ligaments maintain uterine anteversion. Uterine blood supply derives primarily from the anterior division of the internal iliac artery, reaching the organ via the cardinal ligament. Lymphatic drainage maps onto clinical oncological spread, with differing routes for the cervix, corpus, and fundus. Pain pathways follow the pelvic pain line, dictating neuroanatomical targets for obstetric analgesia.
The Uterio bank has 21 questions on this topic. 3 arebelow in full; the syllabus detail is in the Anatomy study guide.
How the exam tests Uterus
- Lymphatic drainage patterns distinguishing corpus, fundus, and cervix spread to pelvic, para-aortic, and superficial inguinal nodes.
- Anatomical relations at the uterine cornu, contrasting the anterior round ligament with the posterior ovarian ligament.
- Arterial microvasculature of the endometrium, specifically distinguishing straight basal arteries from hormone-sensitive spiral arteries.
- Uterine support ligaments, their contents, and their clinical relevance to apical support, ureteric injury, and endometriosis.
High-yield facts
- Basal arteries supply the stratum basalis, do not show cyclical hormonal changes, and regenerate the endometrium after menstruation and parturition.
- The middle interlacing myometrial layer forms living ligatures that mechanically compress traversing spiral vessels to secure postpartum haemostasis.
- In reproductive-aged women, the body-to-cervix length ratio is two to one, which involutes to one to one after menopause.
- The isthmus is a one-centimetre segment between the anatomical and histological internal os that forms the lower uterine segment in pregnancy.
- The uterine artery arises from the anterior division of the internal iliac artery and traverses the cardinal ligament above the ureter.
- The uterine corpus drains primarily along the upper paracervical pathway to the external iliac and obturator lymph nodes.
- Lymphatics from the uterine fundus can travel along the round ligament through the inguinal canal to the superficial inguinal nodes.
- Cervical lymphatics drain initially to the obturator, internal iliac, and external iliac nodes before reaching common iliac stations.
- Visceral pain afferents from the uterine body and fundus travel with sympathetic nerves to enter the spinal cord at T10 to L1.
- The round ligament attaches anterior and inferior to the uterotubal junction, traversing the inguinal canal to insert into the labium majus.
- The uterosacral ligaments anchor the cervix and upper vagina to the sacrum and represent the commonest site of deep infiltrating endometriosis.
- On ultrasound imaging, normal myometrium appears homogeneously hypoechoic relative to the more echogenic central endometrial stripe.
Common pitfalls
- Confusing the round and ovarian ligament attachments at the cornu; the round ligament lies anterior and inferior, while the ovarian ligament lies posterior.
- Assuming the uterine fundus drains exclusively to pelvic nodes, overlooking direct drainage via the ovarian vessels to para-aortic nodes.
- Believing sympathetic innervation provides motor drive for labour, whereas myometrial contractions are primarily myogenic and modulated by oxytocin and prostaglandins.
Practice questions: Uterus
Single best answer, exactly as the exam asks. Commit to an option before opening the explanation.
Question 1
AnatomyWhich arteries directly supply the layer of the endometrium that is not shed at menstruation, and show no cyclical change in response to ovarian hormones?
- ABasal arteries
- BSpiral arteries
- CRadial arteries
- DArcuate arteries
- EUterine arteries
Show answer and explanation
Correct answer: A. Basal arteries
Key takeaway
The basal (straight) arteries arise from the radial arteries at the myometrial–endometrial junction and supply the stratum basalis; they do not change with the cycle, so the basalis survives menstruation and regenerates the functional layer, which is supplied by the hormone-sensitive spiral arteries.
The uterine artery gives arcuate arteries that encircle the uterus in the outer myometrium, and these give radial arteries that run inwards towards the cavity. At the myometrial–endometrial junction each radial artery gives off short, straight basal arteries and then continues as a coiled spiral artery. The basal arteries supply the adjacent myometrium and the stratum basalis, the deepest layer of the endometrium. They show no cyclical response to oestrogen and progesterone, so the basalis keeps its blood supply when the functional layer is shed, and its glands and stroma regenerate the functionalis after each menstruation and after delivery. Damage to the basalis, for example from vigorous curettage of a recently pregnant uterus, can therefore cause intrauterine adhesions (Asherman syndrome).
The spiral arteries supply the functional layer. They lengthen and coil under progesterone in the secretory phase, and their constriction after progesterone withdrawal begins menstrual shedding, so they are the cyclically changing vessels; in pregnancy they are the arteries remodelled by trophoblast. The radial arteries lie in the myometrium and reach the endometrium only through their basal and spiral branches. The arcuate arteries lie in the outer myometrium, and the uterine arteries, from the anterior division of the internal iliac arteries, supply the whole uterus through this branching tree rather than any single layer directly.
Question 2
AnatomyWhich of the following structures is covered by columnar epithelium?
- AThe distal portion of the anal canal
- BThe endocervix
- CThe lung alveoli
- DThe vagina
- EThe urinary ureter
Show answer and explanation
Correct answer: B. The endocervix
Key takeaway
The endocervix is lined by simple columnar, mucus-secreting epithelium. Within the female genital tract, the fallopian tube mucosa is also lined by simple columnar epithelium (ciliated and secretory cells), and so is the uterine endometrium.
Epithelial classifications are a high-yield MRCOG anatomy topic, because epithelial transitions map onto the origin of many gynaecological and GI malignancies.
The endocervix is lined by simple columnar, mucus-secreting epithelium thrown into complex folds (plicae palmatae). Its primary functions are to produce cervical mucus, form the mucus plug of pregnancy, and act as a physiological barrier. The squamocolumnar junction (SCJ) — where this endocervical columnar epithelium meets the ectocervical stratified squamous epithelium — migrates with age and hormonal state, defining the transformation zone (the site of most cervical pre-invasive dysplasia and invasive squamous cell carcinoma).
Other sites lined by columnar epithelium:
- Fallopian tube mucosa — simple columnar, both ciliated and secretory; the ciliary beat and peristalsis together transport the ovum/embryo toward the uterus.
- Endometrium — simple columnar, with glands extending into the stroma; responsive to oestrogen and progesterone.
- Stomach and small/large intestine — simple columnar with specialised cells (parietal, chief, enterocytes, goblet).
- Gallbladder — simple columnar with microvilli.
- Upper respiratory tract and trachea — pseudostratified ciliated columnar with goblet cells.
The other structures:
- Distal anal canal — below the pectinate (dentate) line the anal canal is lined by stratified squamous epithelium, non-keratinised at first and keratinised at the anal verge, where it is continuous with perianal skin. The dentate line marks the approximate embryological boundary between endodermal hindgut and ectodermal proctodeum; the change from columnar to squamous epithelium occurs across a variable anal transitional zone that lies near, but not exactly at, the line.
- Lung alveoli — lined by simple squamous epithelium (type I pneumocytes forming the thin gas-exchange surface, with scattered cuboidal type II pneumocytes producing surfactant).
- Vagina — non-keratinised stratified squamous epithelium. Responds to cyclical oestrogen by thickening and accumulating intracellular glycogen (substrate for lactobacilli → acidic vaginal pH).
- Ureter — transitional epithelium (urothelium). Stretchable, waterproof, continuous from renal calyces through bladder and proximal urethra.
Question 3
AnatomyWhat is the primary lymphatic drainage site for the uterine body?
- APara-aortic nodes
- BInternal iliac nodes
- CSuperficial inguinal nodes
- DExternal iliac nodes
- EDeep inguinal nodes
Show answer and explanation
Correct answer: D. External iliac nodes
Key takeaway
The uterine corpus drains chiefly along the uterine vessels to the external iliac nodes, with the adjacent obturator nodes; lesser routes reach the internal iliac and presacral nodes, the para-aortic nodes along the ovarian vessels and the superficial inguinal nodes along the round ligament.
Lymphatic mapping studies in women with endometrial cancer show that the uterine corpus drains along two paracervical pathways. The upper paracervical pathway runs with the uterine vessels to the external iliac and obturator nodes and is the dominant route, which is why these are the stations sampled at surgical staging. The lower paracervical pathway runs to the internal iliac and presacral nodes. A third route accompanies the ovarian vessels in the infundibulopelvic ligament directly to the para-aortic nodes, and fundal injections can reach para-aortic nodes without passing through the pelvis. A minor route along the round ligament reaches the superficial inguinal nodes.
These pathways overlap, so the cervix and the fundus do not have wholly separate nodal basins. Para-aortic nodes are a secondary station for the corpus rather than its primary drainage; the internal iliac nodes receive the lesser lower paracervical pathway; the superficial inguinal nodes receive only the minor round-ligament route; and the deep inguinal nodes receive lymph from the superficial inguinal group, the glans clitoris and the lower limb rather than the uterine body.
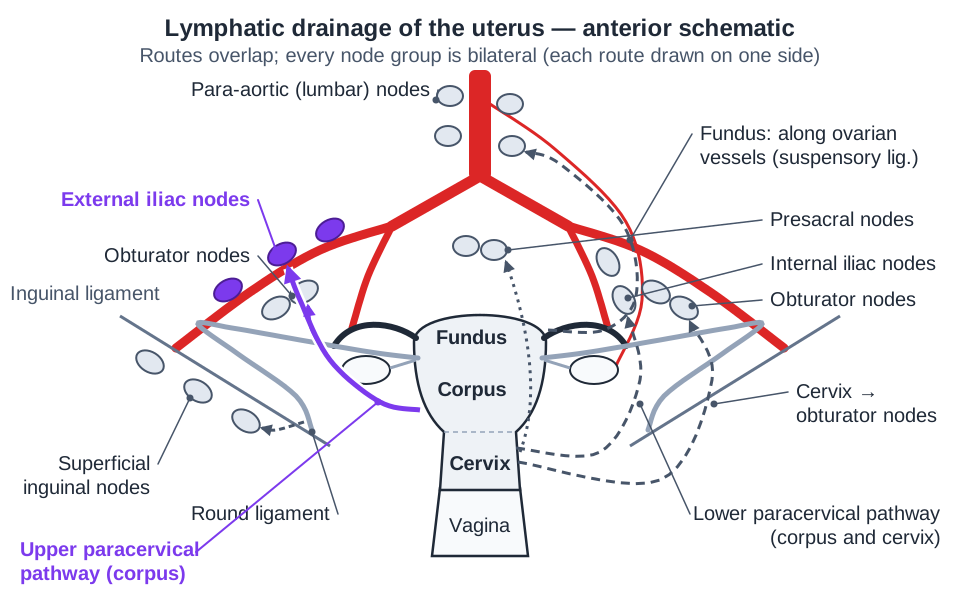 The corpus drains by the upper paracervical pathway to the external iliac and obturator nodes and by the lower pathway to internal iliac and presacral nodes; fundal lymph follows the ovarian vessels to para-aortic nodes and cornual lymph the round ligament to superficial inguinal nodes.
18 more uterus questions in the bank
Every question carries a full explanation and a key takeaway like the ones above. Pay once for 1, 3, 6 or 12 months; no subscription.
What the syllabus covers under uterus
- Structure
- Ligaments
- Blood Supply and Lymphatics
Read the full section in the Anatomy guide, or check the next exam dates.