
MRCOG Part 1 · Anatomy · Anterior Abdominal Wall
Inguinal Region: MRCOG Part 1 questions and key facts
The inguinal region and upper anterior thigh form a critical transition zone between the abdominopelvic cavity and the lower limb. For the gynaecologist and obstetrician, mastering this anatomy is essential for performing safe groin dissections during inguinofemoral lymphadenectomy in vulval cancer, identifying round ligament pathology such as hydroceles of the canal of Nuck, and evaluating groin lumps or hernias in pregnancy. The MRCOG Part 1 examination consistently explores the fascial layers and boundaries of the inguinal canal, the compartments beneath the inguinal ligament, and the structural borders of the femoral triangle and femoral sheath. A precise understanding of neurovascular relations distinguishes competent surgical dissection from inadvertent femoral vessel or nerve injury.
The Uterio bank has 19 questions on this topic. 3 arebelow in full; the syllabus detail is in the Anatomy study guide.
How the exam tests Inguinal Region
- Differentiating fascial origins of the deep and superficial inguinal rings and femoral sheath walls.
- Mapping the structural boundaries and muscular floor of the femoral triangle during lymphadenectomy.
- Recognising neurovascular trajectories through the inguinal canal, notably the ilioinguinal versus genitofemoral nerve.
- Distinguishing femoral and inguinal hernia anatomy in relation to the pubic tubercle and femoral ring.
High-yield facts
- The deep inguinal ring is an aperture in the transversalis fascia located lateral to the inferior epigastric vessels.
- The superficial inguinal ring is a triangular defect in the external oblique aponeurosis lying superior and lateral to the pubic tubercle.
- The conjoint tendon, formed by internal oblique and transversus abdominis aponeuroses, reinforces the posterior wall of the inguinal canal medially.
- The genital branch of the genitofemoral nerve enters the deep ring, whereas the ilioinguinal nerve pierces the internal oblique to enter the canal.
- The iliopectineal arch separates the lateral muscular compartment containing the femoral nerve from the medial vascular compartment beneath the inguinal ligament.
- The femoral sheath is derived from transversalis fascia anteriorly and iliopsoas fascia posteriorly, enclosing the femoral vessels and femoral canal.
- The femoral nerve lies lateral to the femoral sheath, running deep to the iliac fascia in the muscular compartment.
- The femoral ring is bounded by the inguinal ligament anteriorly, the lacunar ligament medially, the pectineal ligament posteriorly, and the femoral vein laterally.
- The femoral canal is the medial compartment of the femoral sheath and typically contains Cloquet's deep inguinal lymph node and lymphatic vessels.
- The femoral triangle boundaries are the inguinal ligament superiorly, the medial border of sartorius laterally, and the medial border of adductor longus medially.
- A femoral hernia emerges below and lateral to the pubic tubercle, whereas an inguinal hernia appears above and medial to the pubic tubercle.
- Incomplete obliteration of the processus vaginalis alongside the round ligament can present as a hydrocele of the canal of Nuck.
Common pitfalls
- Assuming the femoral nerve travels within the femoral sheath; it lies outside, separated by the iliopectineal arch.
- Confusing the roof of the femoral triangle, formed by fascia lata, with its superior border, formed by the inguinal ligament.
- Believing the ilioinguinal nerve enters through the deep inguinal ring rather than piercing the internal oblique muscle directly.
- Misidentifying the medial boundary of the femoral ring as the pectineal ligament rather than the crescent-shaped lacunar ligament.
Practice questions: Inguinal Region
Single best answer, exactly as the exam asks. Commit to an option before opening the explanation.
Question 1
AnatomyThe deep inguinal ring is located in which structure?
- AExternal oblique aponeurosis
- BInternal oblique muscle
- CTransversus abdominis muscle
- DTransversalis fascia
- EInguinal ligament
Show answer and explanation
Correct answer: D. Transversalis fascia
Key takeaway
The deep inguinal ring is an opening in the transversalis fascia, just above the midpoint of the inguinal ligament, and forms the entrance to the inguinal canal.
The inguinal canal is an important anatomical passage in the anterior abdominal wall. It has two main openings: the deep and superficial inguinal rings.
The deep inguinal ring is an opening in the transversalis fascia, a thin layer of fascia lining the inner surface of the transversus abdominis muscle. It serves as the entrance to the inguinal canal. In men, it allows passage of the spermatic cord; in women, the round ligament of the uterus passes through it. It lies about a finger-breadth above the midpoint of the inguinal ligament (halfway between the anterior superior iliac spine and the pubic tubercle), just lateral to the inferior epigastric vessels.
The superficial inguinal ring, on the other hand, is an opening in the external oblique aponeurosis, located just above and lateral to the pubic tubercle. It is the exit point of the inguinal canal.
The external oblique aponeurosis, internal oblique muscle, and transversus abdominis muscle are layers of the abdominal wall that contribute to the formation of the inguinal canal but do not form the deep inguinal ring itself. The inguinal ligament is a thickened lower border of the external oblique aponeurosis, which forms the base of the inguinal canal but not the deep ring.
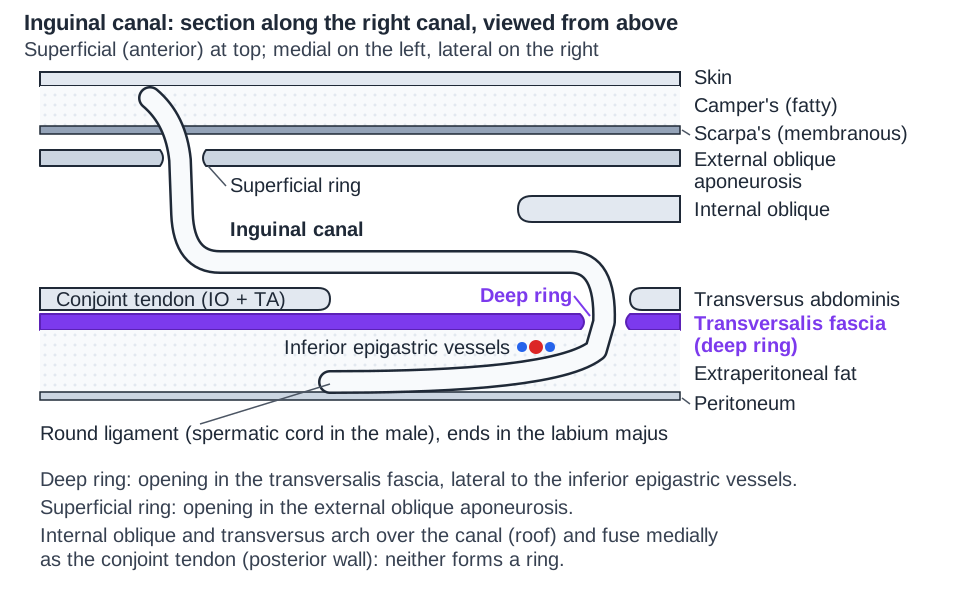 The deep inguinal ring is an opening in the transversalis fascia lateral to the inferior epigastric vessels; the superficial ring is an opening in the external oblique aponeurosis, and internal oblique and transversus arch over the canal without forming a ring.
Question 2
AnatomyDeep to the inguinal ligament, the space between the ligament and the hip bone is divided into a lateral compartment, which transmits iliopsoas and the femoral nerve, and a medial compartment, which transmits the femoral sheath and the femoral vessels. Which structure separates these two compartments?
- AIliopectineal arch
- BIliopubic tract
- CLacunar ligament
- DPectineal ligament
- EFemoral septum
Show answer and explanation
Correct answer: A. Iliopectineal arch
Key takeaway
The iliopectineal arch, a thickened band of iliopsoas fascia running from the back of the inguinal ligament to the iliopubic eminence, divides the space beneath the ligament into a lateral muscular compartment (iliopsoas and the femoral nerve) and a medial vascular compartment containing the femoral sheath.
The gap between the inguinal ligament and the hip bone is the main route from the abdomen and pelvis into the front of the thigh. It is divided into two compartments by the iliopectineal arch, a thickened band of fused iliac and psoas fascia that passes from the deep surface of the inguinal ligament, in front of the femoral nerve, to the iliopubic eminence. Lateral to the arch, the muscular compartment (lacuna musculorum) transmits iliopsoas, the femoral nerve and usually the lateral femoral cutaneous nerve, which sometimes pierces the inguinal ligament instead. Medial to the arch, the vascular compartment (lacuna vasorum) transmits the femoral sheath, which contains the femoral artery, the femoral vein and the femoral canal. Because the arch separates the two, the femoral nerve lies outside the femoral sheath, beneath the iliac fascia, and the arch is occasionally divided to relieve femoral nerve entrapment.
The iliopubic tract is a thickening of the transversalis fascia on the deep surface of the inguinal ligament that arches over the femoral sheath; it is a landmark in laparoscopic hernia repair but does not divide the compartments. The lacunar ligament forms the medial limit of the vascular compartment. The pectineal ligament (Cooper's ligament, often called the iliopectineal ligament in descriptions of colposuspension, but distinct from the arch) runs along the pecten pubis at the back of the vascular compartment. The femoral septum is condensed extraperitoneal tissue that closes the femoral ring at the top of the femoral canal.
Question 3
AnatomyWhich nerve joins the inguinal canal by piercing the internal oblique rather than entering through the deep ring, then exits via the superficial inguinal ring?
- AIliohypogastric nerve
- BIlioinguinal nerve
- CGenital branch of the genitofemoral nerve
- DObturator nerve
- EFemoral nerve
Show answer and explanation
Correct answer: B. Ilioinguinal nerve
Key takeaway
The ilioinguinal nerve (from L1) runs alongside the spermatic cord (male) or round ligament of the uterus (female) through the inguinal canal and exits via the superficial inguinal ring to supply the skin over the anterior scrotum/labia majora and the adjacent upper medial thigh.
Structure of the inguinal canal. The inguinal canal is an oblique passage ~4 cm long in the anterior abdominal wall, extending from the deep inguinal ring (an opening in the transversalis fascia) laterally to the superficial inguinal ring (an opening in the external oblique aponeurosis) medially. Its walls are:
- Anterior wall: external oblique aponeurosis (reinforced laterally by internal oblique)
- Posterior wall: transversalis fascia (reinforced medially by the conjoint tendon)
- Roof: arching fibres of internal oblique and transversus abdominis
- Floor: inguinal ligament (and the lacunar ligament medially)
Contents. In males the canal transmits the spermatic cord and the ilioinguinal nerve; in females it transmits the round ligament of the uterus, the genital branch of the genitofemoral nerve and the ilioinguinal nerve.
The ilioinguinal nerve itself. Originating from L1 of the lumbar plexus, the ilioinguinal nerve pierces internal oblique and runs through the canal alongside the round ligament (or spermatic cord), exiting via the superficial inguinal ring. Its sensory territory is the anterior scrotum/labia majora and the upper medial thigh.
Distinguishing from the genitofemoral nerve (L1–L2): the genital branch of the genitofemoral nerve also accompanies the round ligament (or spermatic cord) along the canal and leaves through the superficial ring, but it enters through the deep inguinal ring, whereas the ilioinguinal nerve pierces internal oblique near the anterior superior iliac spine and enters the canal without passing through the deep ring. The entry route, not the exit, is the discriminator. The genital branch supplies the cremaster muscle in males and a small area of labial skin in females.
The iliohypogastric nerve (T12, L1) runs above the canal and supplies skin over the suprapubic and lateral gluteal regions; it does not enter the canal. The obturator and femoral nerves descend well away from the inguinal canal.
16 more inguinal region questions in the bank
Every question carries a full explanation and a key takeaway like the ones above. Pay once for 1, 3, 6 or 12 months; no subscription.
What the syllabus covers under inguinal region
- Inguinal Ligament
- Inguinal Canal
- Femoral Triangle
Read the full section in the Anatomy guide, or check the next exam dates.